Narrowing of the spinal canal in the neck can pinch nerve roots — or press on the spinal cord itself. Knowing which is happening is everything. Dr. Hobbs provides conservative-first care for nerve symptoms and modern decompression surgery when the cord is at risk.

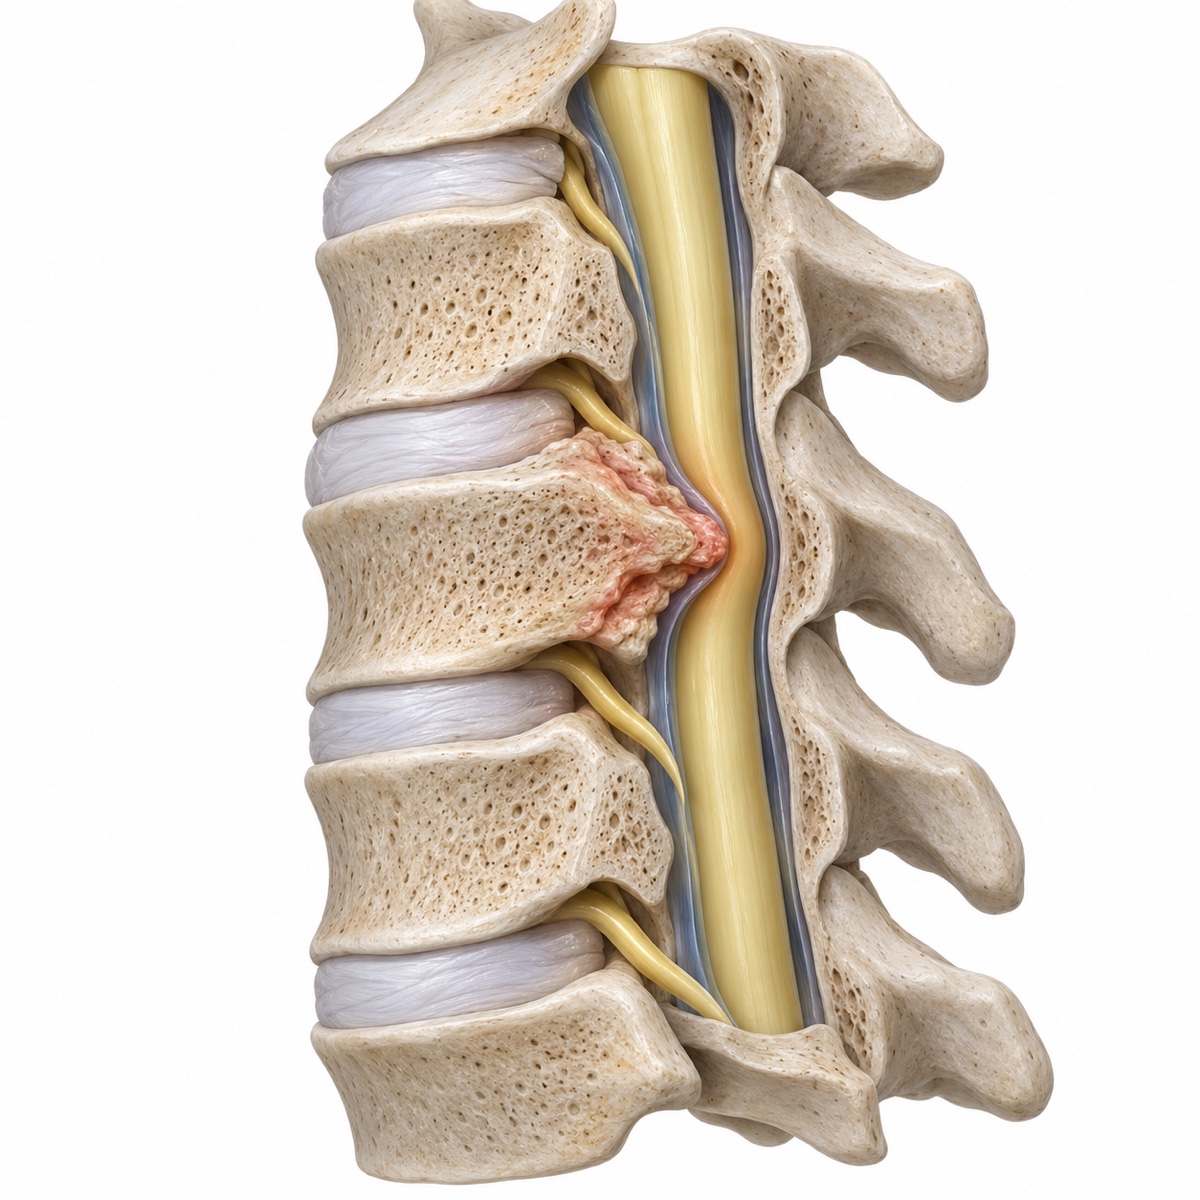
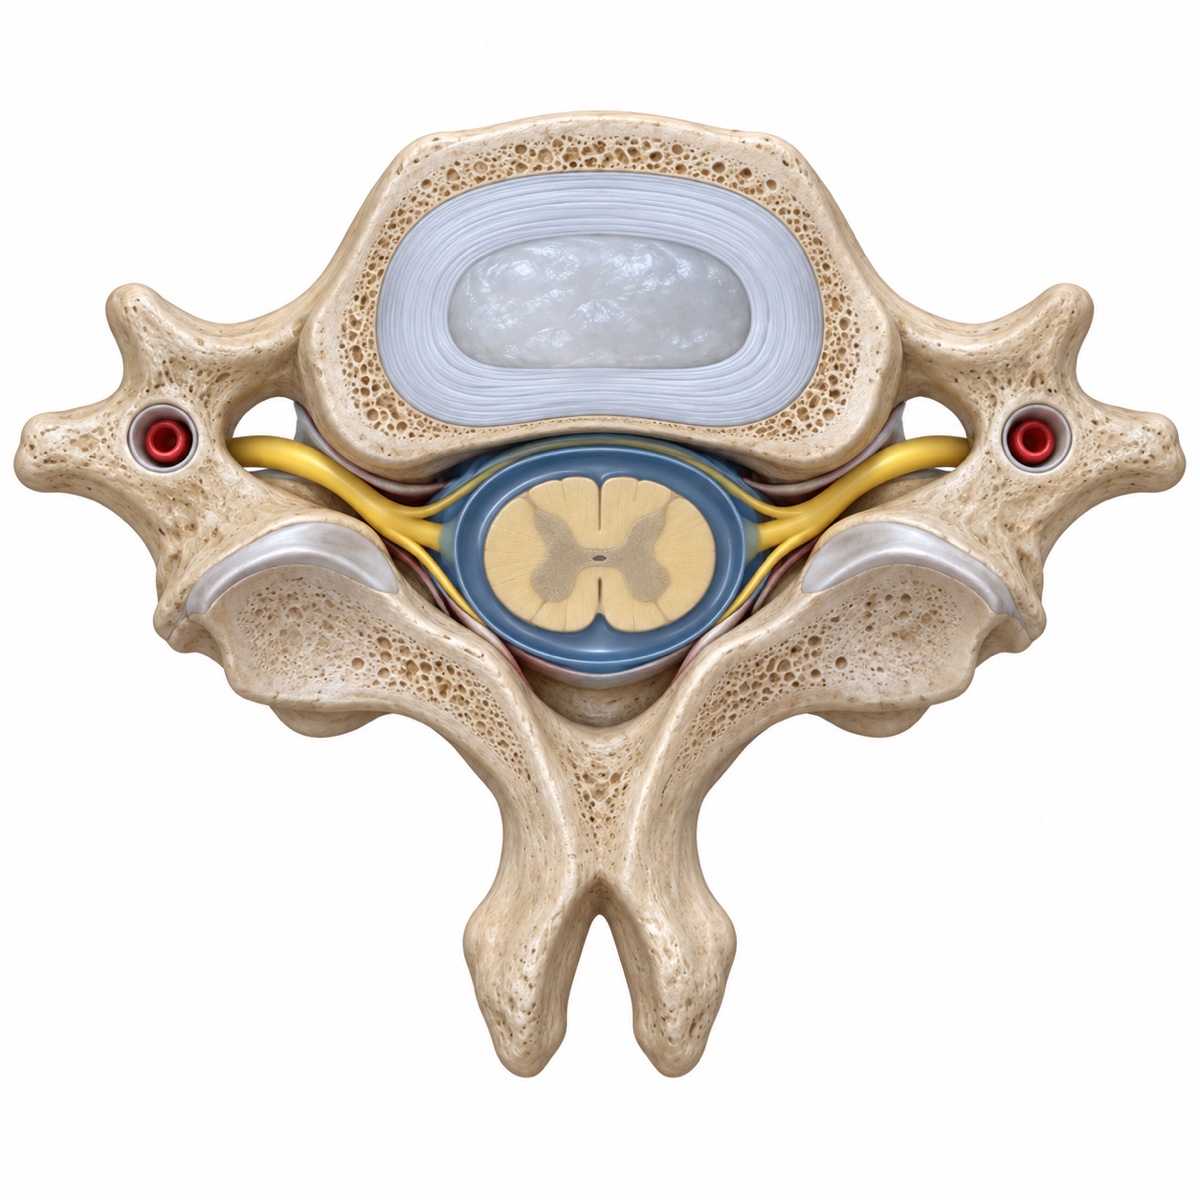
The spinal canal in the neck is a bony tunnel that carries the spinal cord, with side openings where nerve roots exit to the arms. Stenosis is narrowing of that tunnel — usually built slowly over years by bulging discs, thickening ligaments, and bone spurs from arthritis.
Narrowing alone isn’t a disease; many people have it without symptoms. It matters when the space runs out — and what gets compressed determines everything about how it feels and how urgently it’s treated. Pressure on a nerve root causes arm pain and tingling that usually responds to conservative care. Pressure on the spinal cord causes a quieter, more serious problem: cervical myelopathy.
Tap each stage to see what changes inside the canal — and when the problem changes category.

Three illustrative patterns, not inevitable steps. Nerve-root and spinal-cord narrowing can occur separately or together. The examination and MRI establish what is affecting function.
Uncomfortable, and usually manageable with therapy, medication, and injections. See radiculopathy.
Often quiet and painless, which is why it gets missed. See cervical myelopathy.
Check any that apply. Educational only — not a diagnosis; a licensed clinician makes all care decisions.
The dividing line is the spinal cord. When it’s not involved, Dr. Hobbs explores nonsurgical care first — and it usually works.
A neurological exam looks for the subtle signs of cord involvement — reflexes, hand dexterity, gait — and an MRI shows exactly where the canal is narrowed and whether the cord is being pressed.
Radiating arm symptoms are given a real trial of therapy, medication, and injections. Most improve. Surgery is considered only if symptoms persist or weakness progresses.
When the cord is compressed and function is declining, the goal shifts from relieving pain to preserving what the cord can still do. Decompression is planned promptly rather than watched.
When conservative care isn’t enough — or when the spinal cord is compressed and function is declining — surgery restores the space:

ABNS
Residency
M.D.Trained specifically in surgery of the spinal cord and nerves, so the nerve-versus-cord call is made by a specialist in both.
University of Kentucky medical degree; University of Chicago neurosurgery residency, chief resident.
Navigation-guided, tissue-sparing decompression tailored to the pattern of narrowing — from the front, the back, or both.
Surgery only when conservative care can’t protect your function.
Certified by the American Board of Neurological Surgery.
Practicing at Northwest Indiana's most preferred orthopedic and spine practice, with offices in Crown Point & Chesterton.
Nerve or cord — the answer changes everything about treatment and urgency. Get a clear diagnosis from a neurosurgeon who treats both.
(219) 250-5010Monday – Friday · 8:00 AM – 4:30 PM
500 E. 109th Avenue
Crown Point, IN 46307
601 Gateway Boulevard
Chesterton, IN 46304
Your next step
Jonathan G. Hobbs, M.D. is a board-certified neurosurgeon at Lakeshore Bone & Joint Institute. For questions about cervical spinal stenosis, call the office to arrange an individual evaluation and discuss which options may be appropriate.
Consultation offices: Crown Point, Chesterton. Your symptoms, examination, imaging, and prior treatment help guide the discussion.
Page updated . About content and medical review dates.