Now accepting new patients Crown Point & Chesterton, Indiana
Home /Conditions /Cervical Myelopathy
Neurosurgical Care

Cervical Myelopathy

Spinal cord compression in the neck rarely announces itself with pain. It shows up as clumsy hands, unsteady walking, and dropped objects — and it is one of the most commonly missed spine diagnoses. Dr. Hobbs provides the neurosurgical evaluation and modern decompression surgery this condition demands.

Call (219) 250-5010
Cervical myelopathy · the spinal cord

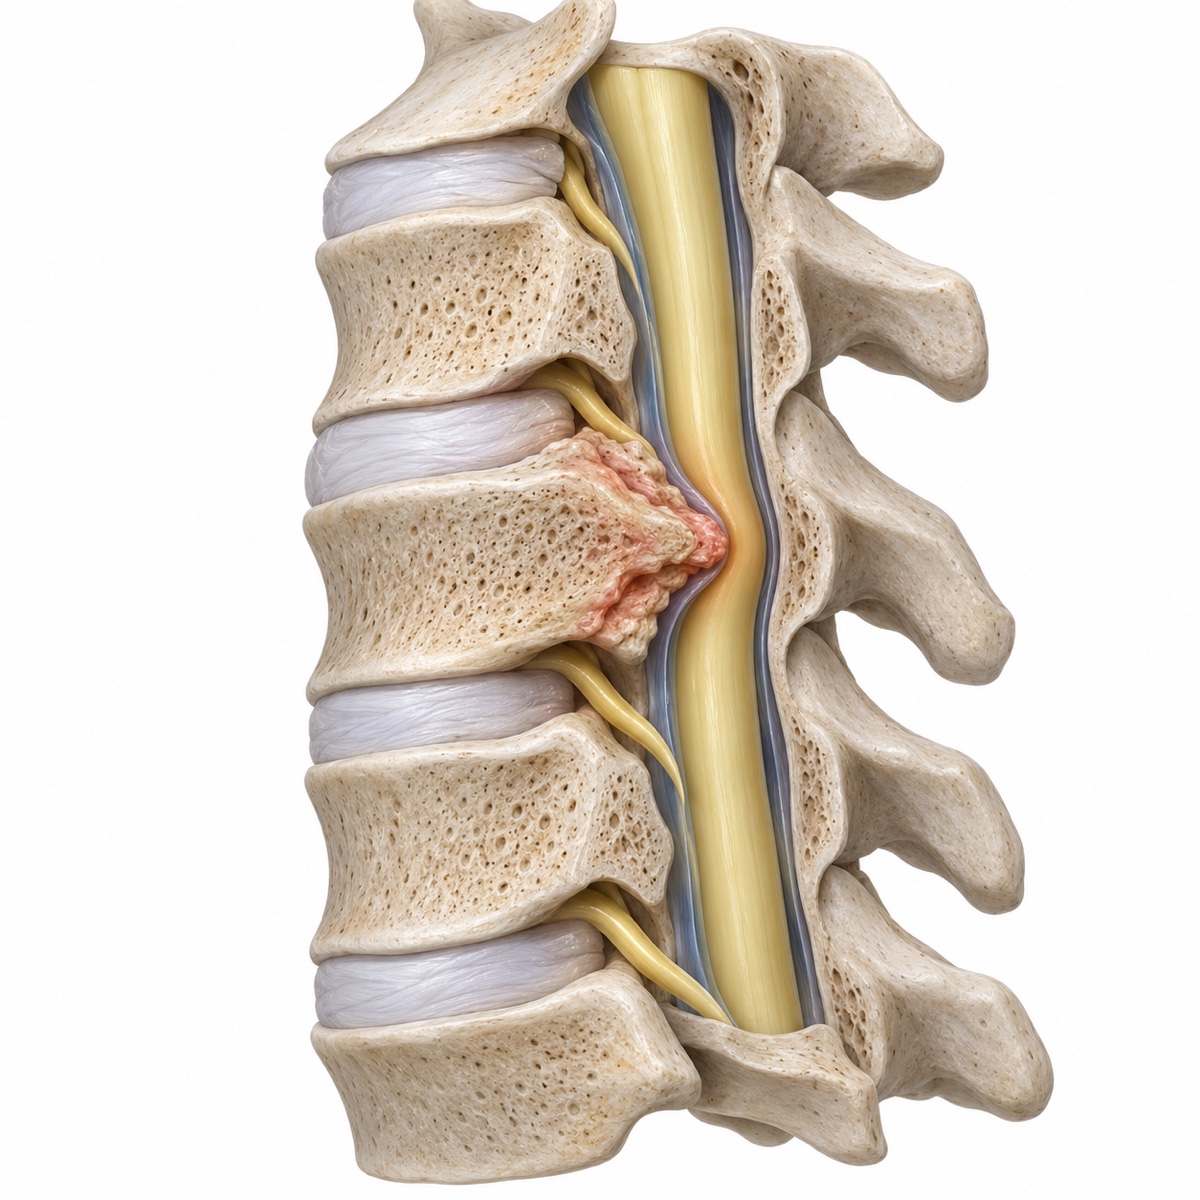
Three-dimensional neck anatomy showing a disc and bone-spur ridge narrowing the canal beside the spinal cord
A neck problem can affect more than the neck.The spinal cord carries signals to the hands and legs. Pressure here can affect coordination and walking. Educational illustration.
Often painless. Clumsy hands and an unsteady walk are the usual first signs, not neck pain.
Progressive. The cord does not tolerate compression indefinitely; timing matters.
Cord expertise. Surgery of the spinal cord is core neurosurgical territory.
Medically reviewed by Jonathan G. Hobbs, M.D. · Updated July 2026
The condition

What Is Cervical Myelopathy?

Cervical myelopathy is compression of the spinal cord in the neck. It usually develops gradually from age-related change — bulging discs, thickened ligaments, and bone spurs slowly narrowing the canal the spinal cord runs through. Because the cord carries the signals for everything below the neck, compression shows up far from the neck itself: in the hands, the legs, and the sense of balance.

Two things make myelopathy different from most spine problems. First, it is often painless — many patients never connect their clumsy hands or unsteady walk to their neck. Second, it is progressive: the cord does not tolerate compression indefinitely, and function lost is harder to recover than function protected. Both are reasons this diagnosis belongs in front of a neurosurgeon early.

Stenosis describes the space. Myelopathy describes the effect on function.Narrowing on a scan does not, by itself, establish myelopathy. Dr. Hobbs matches the scan with changes in coordination, strength, reflexes, and walking.
Compare the canal views
Interactive — connect the task to the body

Where Myelopathy Shows Up First

Choose an everyday task to see the function it relies on, and why a problem in the neck may be noticed in the hands or legs.

Hands & fine controlFront view
Cervical cord compression can affect hands & fine controlCoral marks the neck. Gold highlights the hands to illustrate function that can be affected. Lines show a simplified connection, not individual nerve anatomy or a pain map.
Function being explored Cervical cord
Both hands may be affected because their signals pass through the spinal cord in the neck. Symptoms can be uneven.
Buttoning a shirt Fine motor control of the fingers depends on clean signals through the spinal cord’s corticospinal tracts. As compression degrades those signals, precise fingertip work — buttons, zippers, clasps — is often the very first thing to suffer. Patients frequently switch to pullovers without ever wondering why.

Gold marks the part of the body involved in the selected task. This is a function map, not a pain map or a diagnostic test. Symptoms can have other causes; the examination and MRI help establish the source.

How Dr. Hobbs evaluates these changes

Symptoms

Symptoms of Cervical Myelopathy

  • Clumsiness or weakness in the hands — buttons, handwriting, dropping objects
  • Numbness or tingling in the hands or arms
  • Unsteady or wide-based walking; a new need for handrails
  • Stiff or heavy-feeling legs
  • Neck pain or stiffness — present in some, absent in many
  • In advanced cases, bladder urgency or bowel changes

Quick Symptom Self-Check

Check any that apply. Educational only — not a diagnosis; a licensed clinician makes all care decisions.

Select any symptoms above to see general guidance.

Seek Prompt Care

Rapidly progressive weakness, new loss of bladder or bowel control, or sudden decline after a fall or neck injury warrants immediate emergency evaluation — call 911 or go to the ER.

Diagnosis

How Cervical Myelopathy Is Diagnosed

Diagnosis combines a neurological examination — testing reflexes, coordination, gait, and specific cord-compression signs — with MRI of the cervical spine, which shows the cord, the degree of compression, and any signal change within the cord itself. When the picture is unclear, nerve studies (EMG) help distinguish cord compression from peripheral nerve problems like carpal tunnel syndrome, which can mimic early myelopathy.

Because the hallmark of myelopathy is change over time, Dr. Hobbs also documents a functional baseline — so that any future progression is caught objectively, not guessed at.

01Neurological examination

Reflexes, coordination, gait, and the specific signs of cord compression.

02Cervical MRI

Shows the cord, the degree of compression, and any signal change within the cord itself.

03Functional baseline

Documented so that any future progression is caught objectively, not guessed at.

See these structures on a cervical MRI.

Switch between a side view and a cross-section, then explore the cord, discs, and fluid space.

Explore the MRI guide
Treatment

Treatment Options

Myelopathy is treated differently from most spine conditions: because compression injures the cord cumulatively, documented progression generally calls for surgical decompression — the goal is to stop further loss of function.

Mild and stable

Active Monitoring

Mild myelopathy that is not progressing may be monitored closely with scheduled exams and imaging, along with activity guidance to protect the neck. Monitoring is an active plan — not a dismissal — and the threshold for acting is any documented decline.

Documented progression

Decompression Surgery

Surgery creates space for the spinal cord and halts ongoing injury. Depending on where and how the cord is compressed, Dr. Hobbs tailors the approach:

  • Anterior approaches — removing compressing disc and bone from the front of the neck, with reconstruction of the segment
  • Posterior approaches — laminectomy or laminoplasty to open the canal from behind when compression spans multiple levels
  • Precision technique — image-guided navigation and tissue-sparing approaches where the anatomy allows
Jonathan G. Hobbs, M.D.
Board-Certified Neurosurgeon · Spine Surgery
American Board of Neurological SurgeryABNS
Certified
The University of ChicagoResidency
Chicago
University of KentuckyM.D.
Kentucky
Why Dr. Hobbs

Why Choose Dr. Hobbs for Myelopathy Care

  • Neurosurgeon — Cord Expertise

    Surgery of the spinal cord is core neurosurgical territory; myelopathy is treated by protecting the cord.

  • Elite Training

    University of Kentucky medical degree; University of Chicago neurosurgery residency, chief resident.

  • Modern Technique

    Image-guided navigation and tissue-sparing approaches tailored to each pattern of compression.

  • Early, Objective Diagnosis

    Functional baselines and scheduled follow-up, so progression is caught, not guessed at.

Frequently Asked Questions About Cervical Myelopathy

Compression of the spinal cord in the neck, most often from age-related degeneration narrowing the spinal canal. Because the cord carries signals for everything below the neck, compression affects the hands, legs, balance, and sometimes bladder function — often with little or no neck pain, which is why it is so commonly missed.
Everyday tasks reveal it first: difficulty buttoning shirts, deteriorating handwriting, dropping objects, trouble with coins, and subtly unsteady walking. Numbness in the hands and stiff-feeling legs are also common. Pain is often mild or absent.
Cord compression does not resolve on its own, and myelopathy tends to progress stepwise — stability interrupted by declines. Mild, non-progressive cases may be monitored closely; documented progression generally calls for surgical decompression to stop further loss of function.
Not always — but unlike most spine conditions, myelopathy is one where surgery plays a central role. When symptoms progress, decompression is the standard of care because it halts ongoing cord injury. Dr. Hobbs tailors the approach — anterior, posterior, or both — to each pattern of compression.
The primary, reliable goal is to stop progression. Many patients also recover meaningful function — better hand dexterity, steadier walking — particularly when surgery comes earlier in the course. Function preserved is more predictable than function recovered, which is why timely diagnosis matters so much.

Don’t Wait on Clumsy Hands.

Myelopathy is progressive — and function protected early beats function chased later. If everyday tasks are getting harder, get evaluated now.

(219) 250-5010

Monday – Friday · 8:00 AM – 4:30 PM

Crown Point Office

500 E. 109th Avenue
Crown Point, IN 46307

Chesterton Office

601 Gateway Boulevard
Chesterton, IN 46304

Your next step

Discuss your spine care with Dr. Hobbs

Jonathan G. Hobbs, M.D. is a board-certified neurosurgeon at Lakeshore Bone & Joint Institute. For questions about cervical myelopathy, call the office to arrange an individual evaluation and discuss which options may be appropriate.

Consultation offices: Crown Point, Chesterton. Your symptoms, examination, imaging, and prior treatment help guide the discussion.

Request a free second-opinion review

Page updated . About content and medical review dates.