Now accepting new patients Crown Point & Chesterton, Indiana
Home /Conditions /Failed Back Surgery Syndrome
Revision Expertise Straight answers

Still in Pain After Back Surgery?

Pain after spine surgery has a reason — and finding it is a specialty of its own. Dr. Hobbs focuses on revision spine surgery: a careful, honest workup of why the first operation didn’t deliver, and a clear plan for what can.

Jonathan G. Hobbs, M.D., neurosurgeon
Revision-focusedMinimally invasive and revision spine surgery are the core of Dr. Hobbs’s practice — and so is telling you when more surgery is not the answer
Not one diagnosis. “Failed back surgery” is an umbrella over six distinct, identifiable problems, each with a different fix.
Records before scalpels. Operative reports, old and new imaging, and your symptom timeline come before any talk of another operation.
Revision only with a target. When the workup finds a structural cause, it is fixed. When it doesn’t, you hear that plainly.
Medically reviewed by Jonathan G. Hobbs, M.D. · Updated July 2026
The condition

What Is Failed Back Surgery Syndrome?

Failed back surgery syndrome (FBSS) — also called post-laminectomy syndrome — is the medical term for persistent or returning pain after spine surgery. The name is misleading in one important way: FBSS is not a single diagnosis. It is an umbrella over many distinct, identifiable problems, each with a different solution.

That is why the evaluation matters more than anything else. Before talk of another operation, Dr. Hobbs works to answer one question precisely: why didn’t the first surgery work? Sometimes the answer leads to a targeted revision. Sometimes it leads away from surgery entirely. Either way, patients leave with clarity.

The worst outcome after a failed surgery is a second one that had no reason to succeed.

The principle behind every revision workup

Interactive — pick a cause

Why Back Surgery Fails

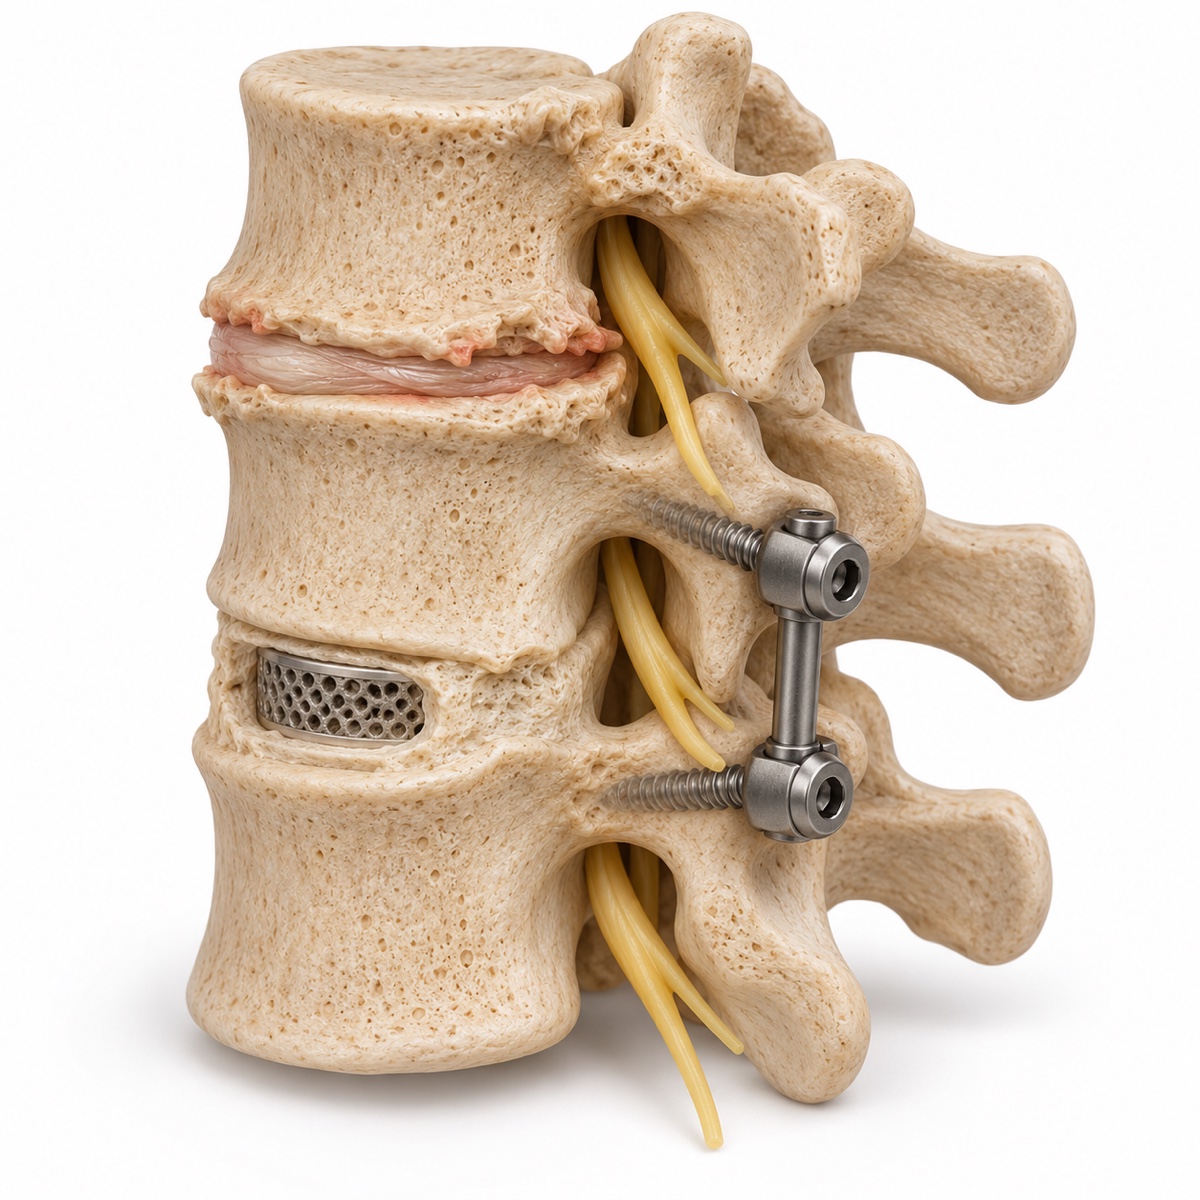
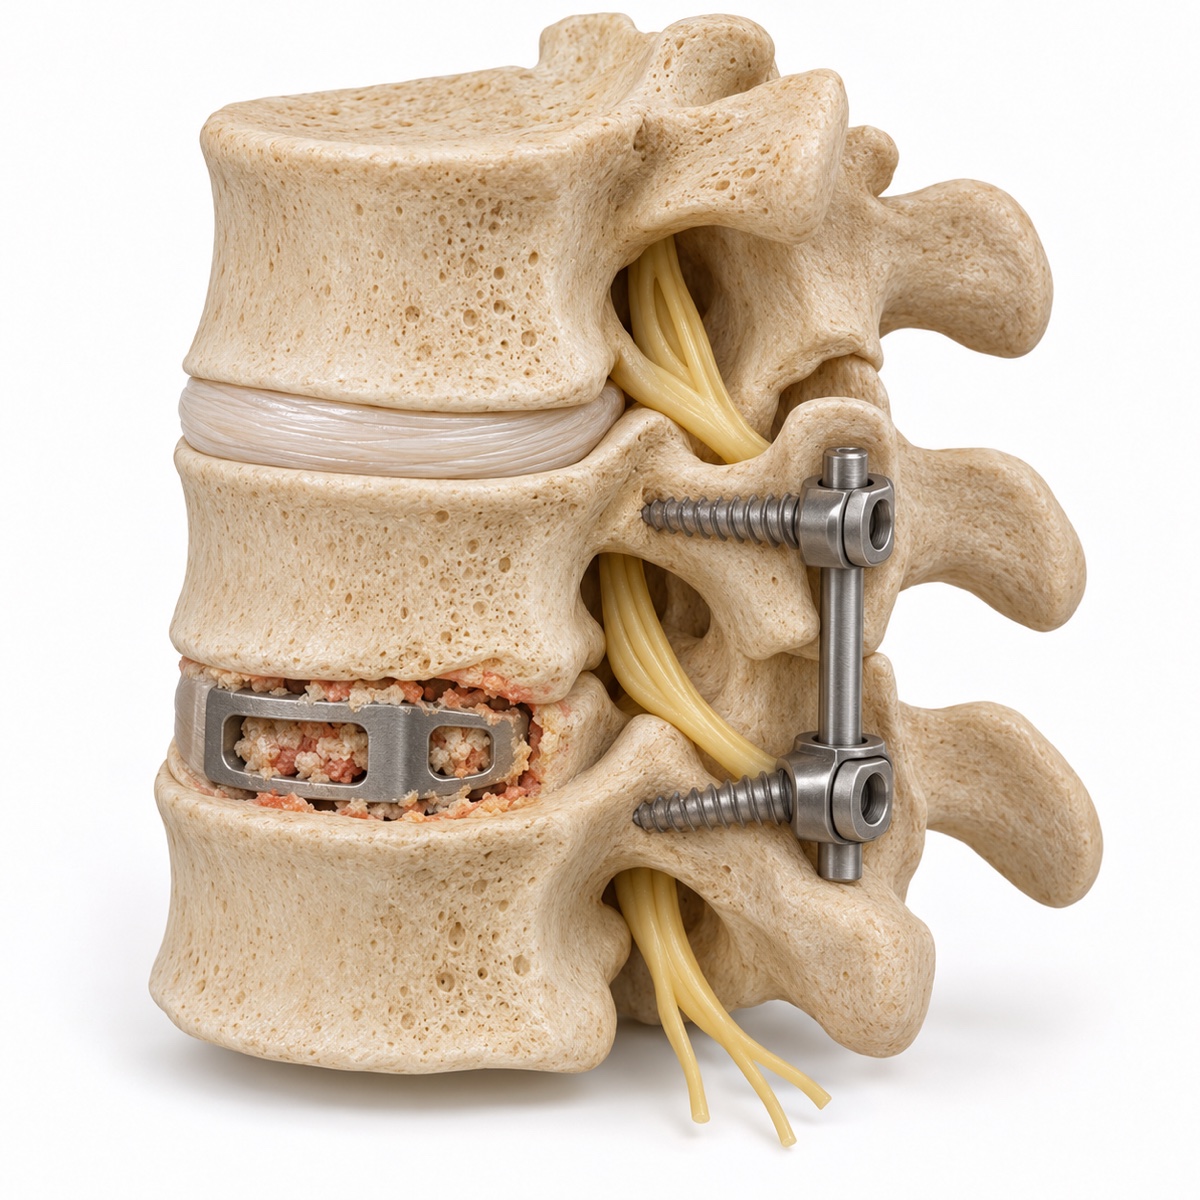
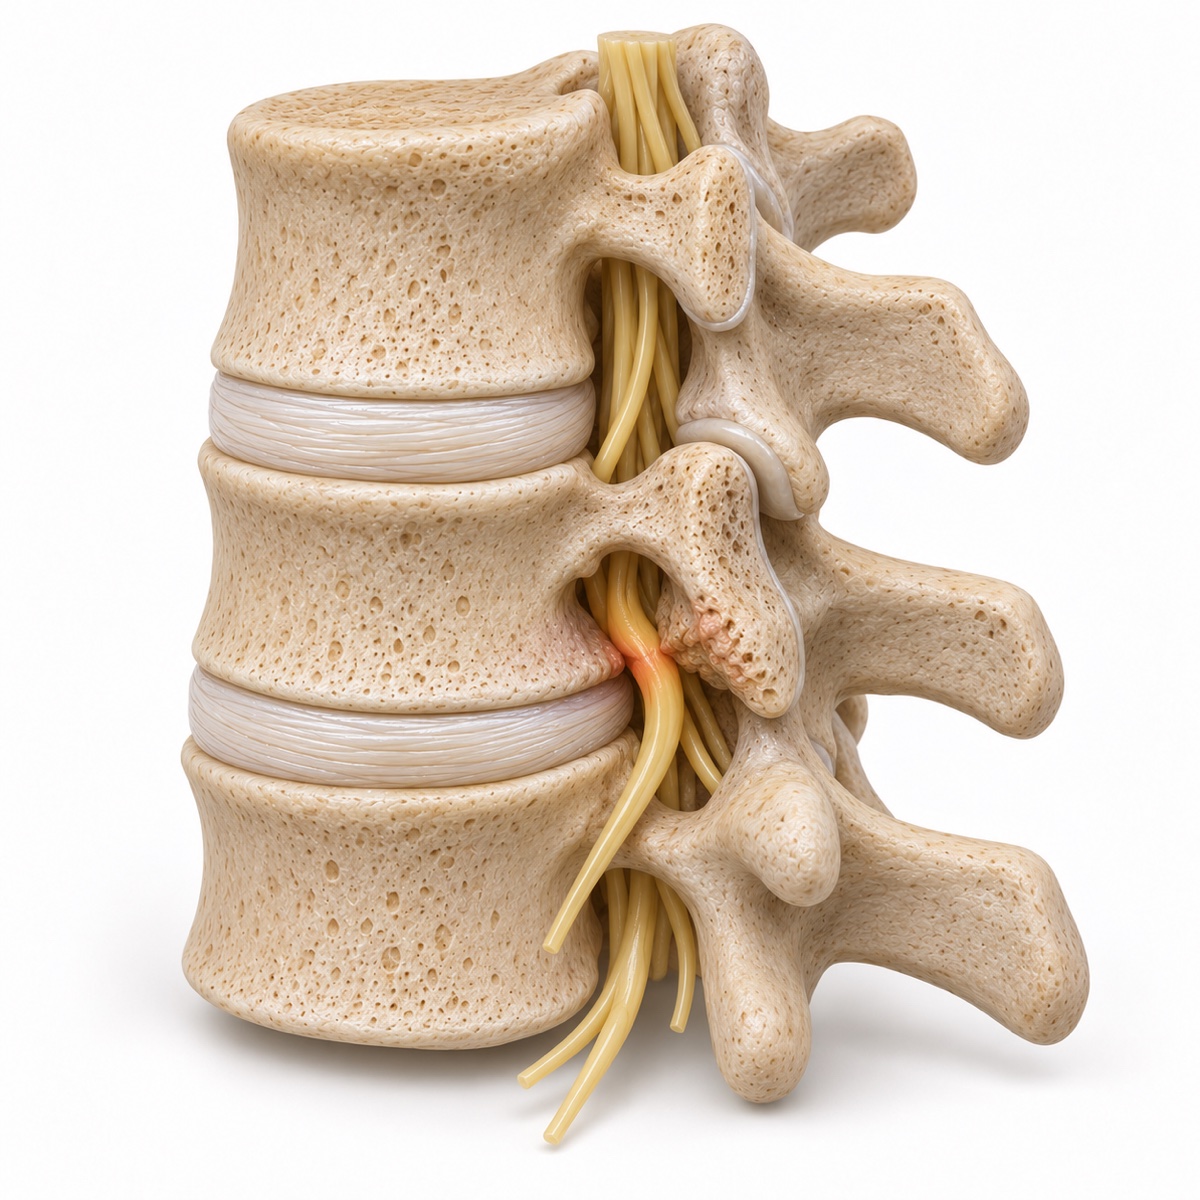
Six problems account for most pain after spine surgery. Tap each one to see where it lives, what it feels like, and how it is addressed.

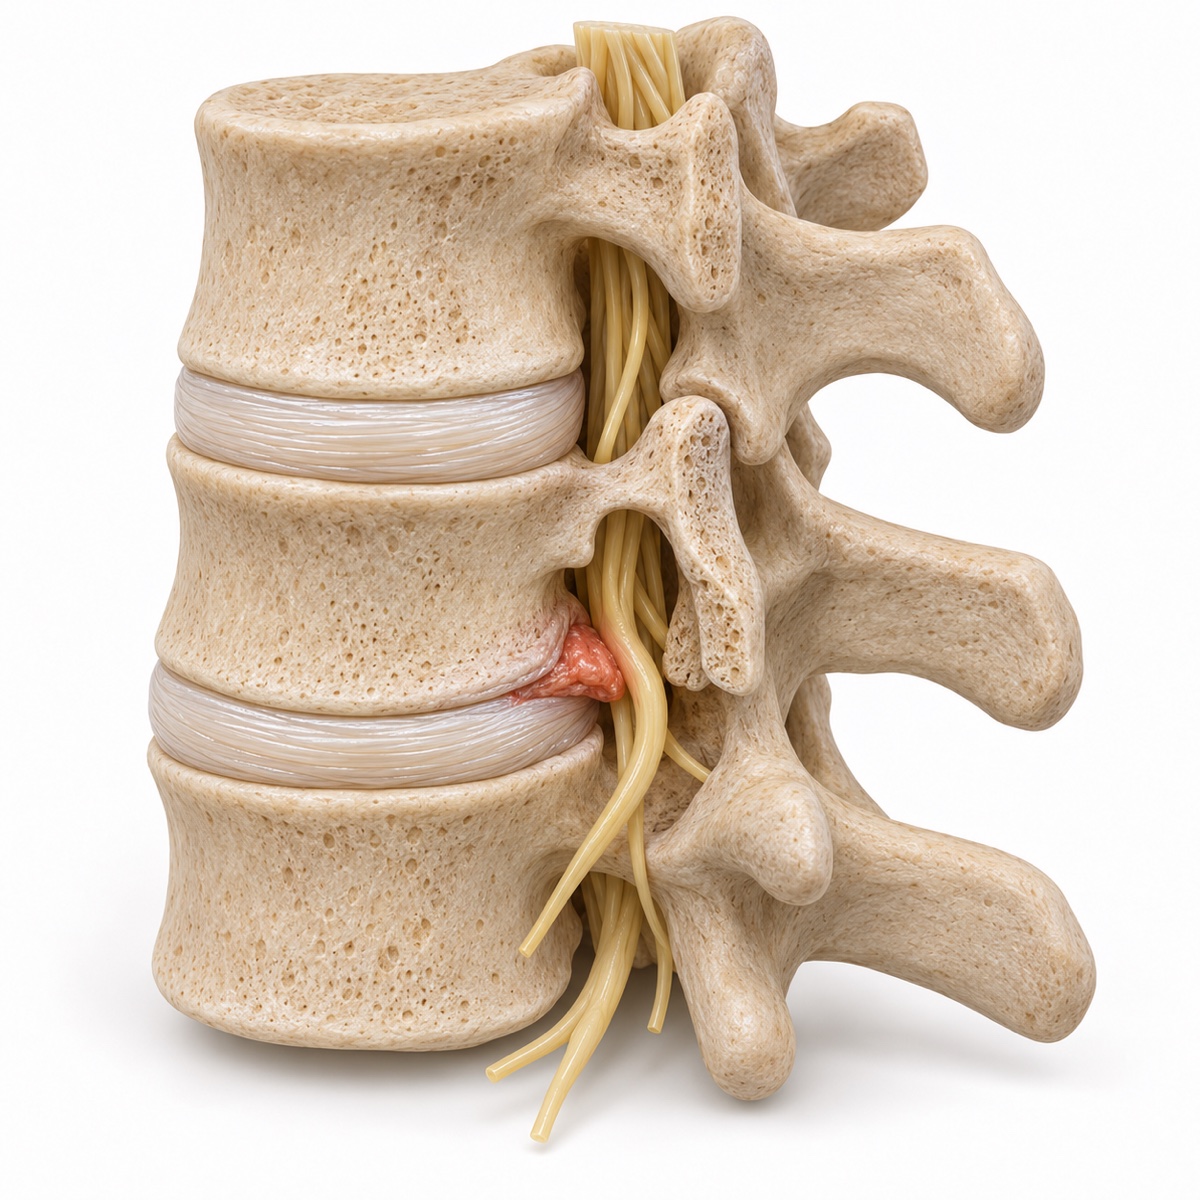
Recurrent herniation3D anatomy · side view
Three-dimensional lumbar anatomy showing a recurrent coral-colored disc fragment at the operated level beside a yellow nerve root
Recurrent disc fragmentThe coral fragment shows disc material pressing toward a nearby nerve.
The same disc herniates again at the operated level
Recurrent disc herniation The same disc herniates again at the operated level — classically after a period of real relief, then a return of the familiar leg pain. Imaging with contrast distinguishes a new fragment from scar tissue, and a repeat microdiscectomy is often curative when a true recurrence is found.

3D illustrations for education — not actual scans or a diagnosis. Scar tissue is a seventh, less common contributor that imaging with contrast helps identify.

Symptom patterns

Patterns That Point to the Cause

How your pain behaved after surgery is diagnostic gold. The pattern narrows the list before a single scan is ordered.

Relief, then the same pain returned

Suggests recurrence at the operated level.

Never really improved

Raises the question of residual compression or a different pain source.

New, different pain months or years later

Points toward the adjacent level or hardware.

Deep, aching pain with activity after fusion

Can indicate a fusion that hasn’t fully healed.

Quick self-check

Is a Revision Evaluation Worth It?

Check any that apply. Educational only — not a diagnosis; a licensed clinician makes all care decisions.

Select any that apply to see general guidance.
The workup

The Revision Workup

A revision evaluation is a reconstruction of the whole story. The goal is a specific structural answer.

01

Your Records

Your original operative reports — what was done, and why — plus imaging from before and after surgery.

02

Your Timeline

The precise course of your symptoms: improved and returned, never improved, or changed character. Each pattern narrows the list.

03

New Imaging

MRI with contrast to distinguish scar tissue from recurrent disc material, and CT to assess fusion healing and hardware position.

When a structural answer exists, revision has a clear target. When one doesn’t, Dr. Hobbs says so — because the worst outcome after a failed surgery is a second one that had no reason to succeed.

Treatment

Treatment Options

When the workup finds no surgical target

When Surgery Isn’t the Answer

Not every post-surgical pain has a surgical solution. Structured physical therapy, targeted injections, and coordinated pain management often deliver meaningful relief — and an honest “no more surgery” is itself a diagnosis worth having.

When a structural cause is identified

Revision Spine Surgery

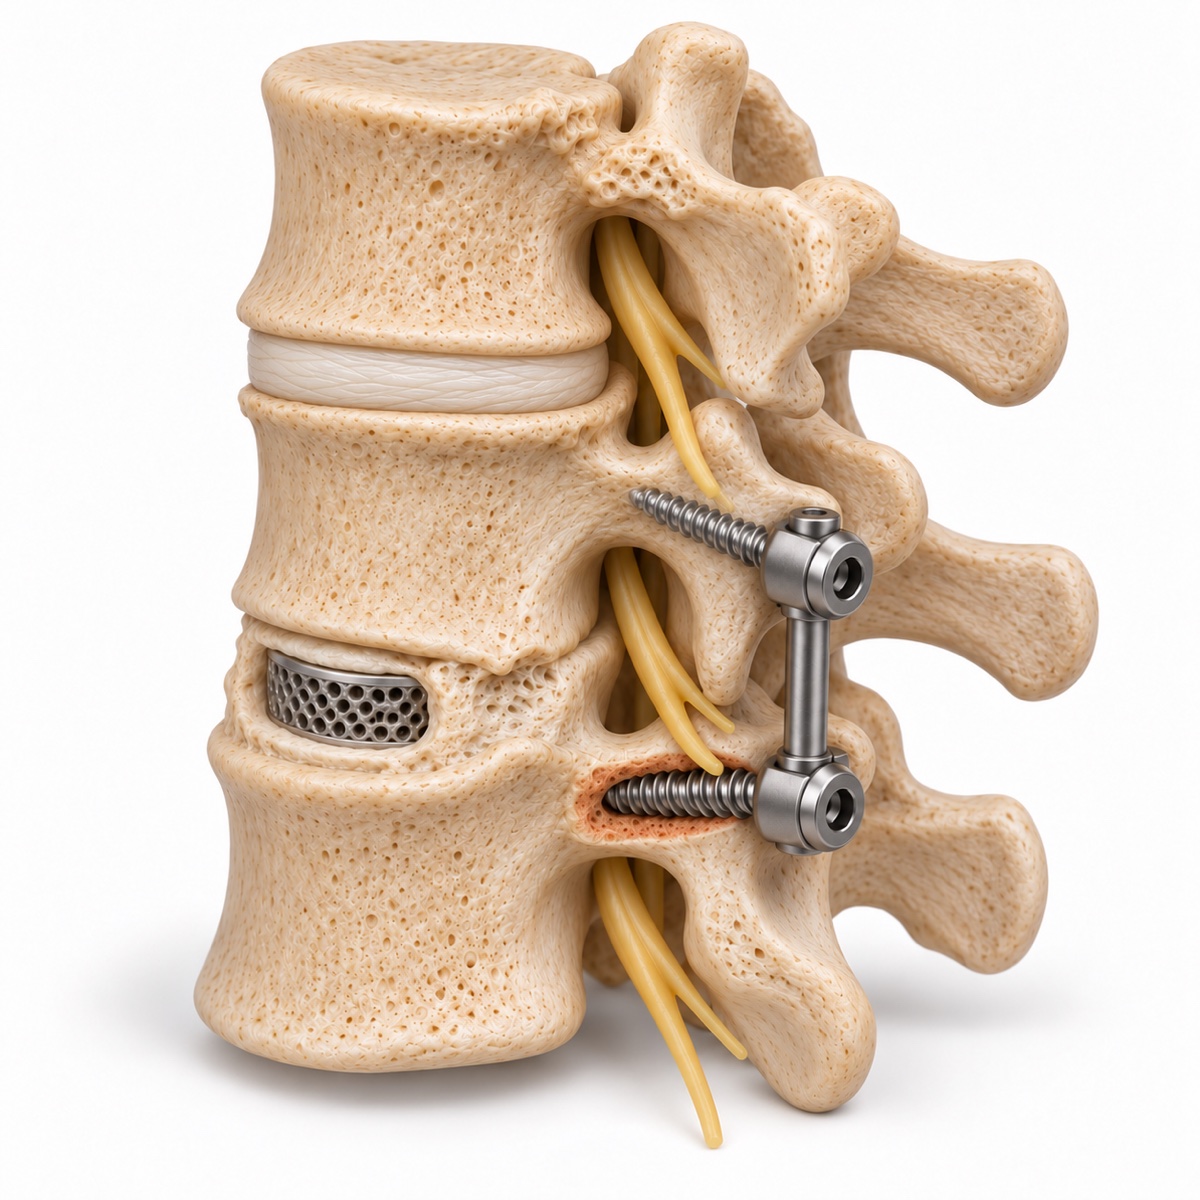
Revision surgery addresses the cause directly — repeat decompression for recurrent herniation or residual stenosis, repair of an unhealed fusion, extension or removal of hardware, or treatment of the adjacent level. Operating in previously operated anatomy demands precision, which is why Dr. Hobbs uses image-guided navigation in revision cases.

Learn about revision spine surgery
Procedures & resources

What a Revision Can Involve

Each cause has its own fix. These are the procedures Dr. Hobbs draws on once the workup has named the problem.

Was the original surgery part of a work injury?

Dr. Hobbs sees injured workers whose first operation did not resolve the problem. The same honest workup applies, with the reports and communication your adjuster and case manager need.

Workers’ compensation
Jonathan G. Hobbs, M.D.
Board-Certified Neurosurgeon · Spine Surgery
American Board of Neurological SurgeryABNS
Certified
The University of ChicagoResidency
Chicago
University of KentuckyM.D.
Kentucky
Why Dr. Hobbs

Why Choose Dr. Hobbs After a Failed Surgery

  • Revision Focus

    Minimally invasive and revision spine surgery are the core of his practice.

  • Board-Certified Neurosurgeon

    Certified by the American Board of Neurological Surgery.

  • Elite Training

    University of Kentucky medical degree; neurosurgery residency at the University of Chicago, serving as chief resident.

  • Navigation in Scarred Anatomy

    Image-guided precision where landmarks have changed from prior surgery.

  • Honest Evaluation

    Revision only when the workup shows a clear target — and a straight answer when it doesn’t.

  • Lakeshore Bone & Joint Institute

    Practicing at Northwest Indiana's most preferred orthopedic and spine practice, with offices in Crown Point & Chesterton.

Frequently Asked Questions About Failed Back Surgery

The term for persistent or returning pain after spine surgery. It is not one diagnosis — it is an umbrella for many distinct, identifiable problems: recurrent herniation, an unhealed fusion, adjacent segment wear, residual compression, hardware issues, or scar tissue. The essential step is a careful workup to find which problem is present, because each has a different solution.
Common reasons: recurrent disc herniation at the same level, degeneration at the level next to a fusion, a fusion that never fully healed (pseudarthrosis), stenosis that was not fully relieved, hardware loosening, epidural scar tissue — and cases where the operated level was never the true pain source in the first place.
Often, yes — when a structural cause is identified. Revision surgery can address recurrent herniations, unhealed fusions, adjacent segment disease, and residual compression. Just as importantly, an honest evaluation sometimes shows that more surgery is not the answer — and that structured conservative care is the better path.
Prior operative reports, imaging from before and after your surgery, and a clear timeline of how your symptoms behaved — improved and returned, never improved, or changed character. These details narrow the diagnosis dramatically.
Revision surgery is generally more complex because of scar tissue and altered anatomy — which is why it belongs with a surgeon who focuses on it. Dr. Hobbs uses image-guided navigation for precision in previously operated anatomy, and recommends revision only when the workup shows a clear structural target.

Get a Straight Answer About Your Back.

One failed surgery doesn’t mean the story is over. Bring your records — Dr. Hobbs will tell you exactly what he sees, and what can be done about it.

(219) 250-5010

Monday – Friday · 8:00 AM – 4:30 PM

Crown Point Office

500 E. 109th Avenue
Crown Point, IN 46307

Chesterton Office

601 Gateway Boulevard
Chesterton, IN 46304

Your next step

Discuss your spine care with Dr. Hobbs

Jonathan G. Hobbs, M.D. is a board-certified neurosurgeon at Lakeshore Bone & Joint Institute. For questions about still in pain after back surgery?, call the office to arrange an individual evaluation and discuss which options may be appropriate.

Consultation offices: Crown Point, Chesterton. Your symptoms, examination, imaging, and prior treatment help guide the discussion.

Request a free second-opinion review

Page updated . About content and medical review dates.