Now accepting new patients Crown Point & Chesterton, Indiana
Home /Conditions /Spinal Fractures
Spine Condition

Spinal Fractures & Compression Fractures

Sudden back pain after a fall — or in fragile bone, after something as small as a cough — can mean a broken vertebra. Dr. Hobbs evaluates spinal fractures, confirms whether the spine is stable, and treats them with the least invasive option that protects it.
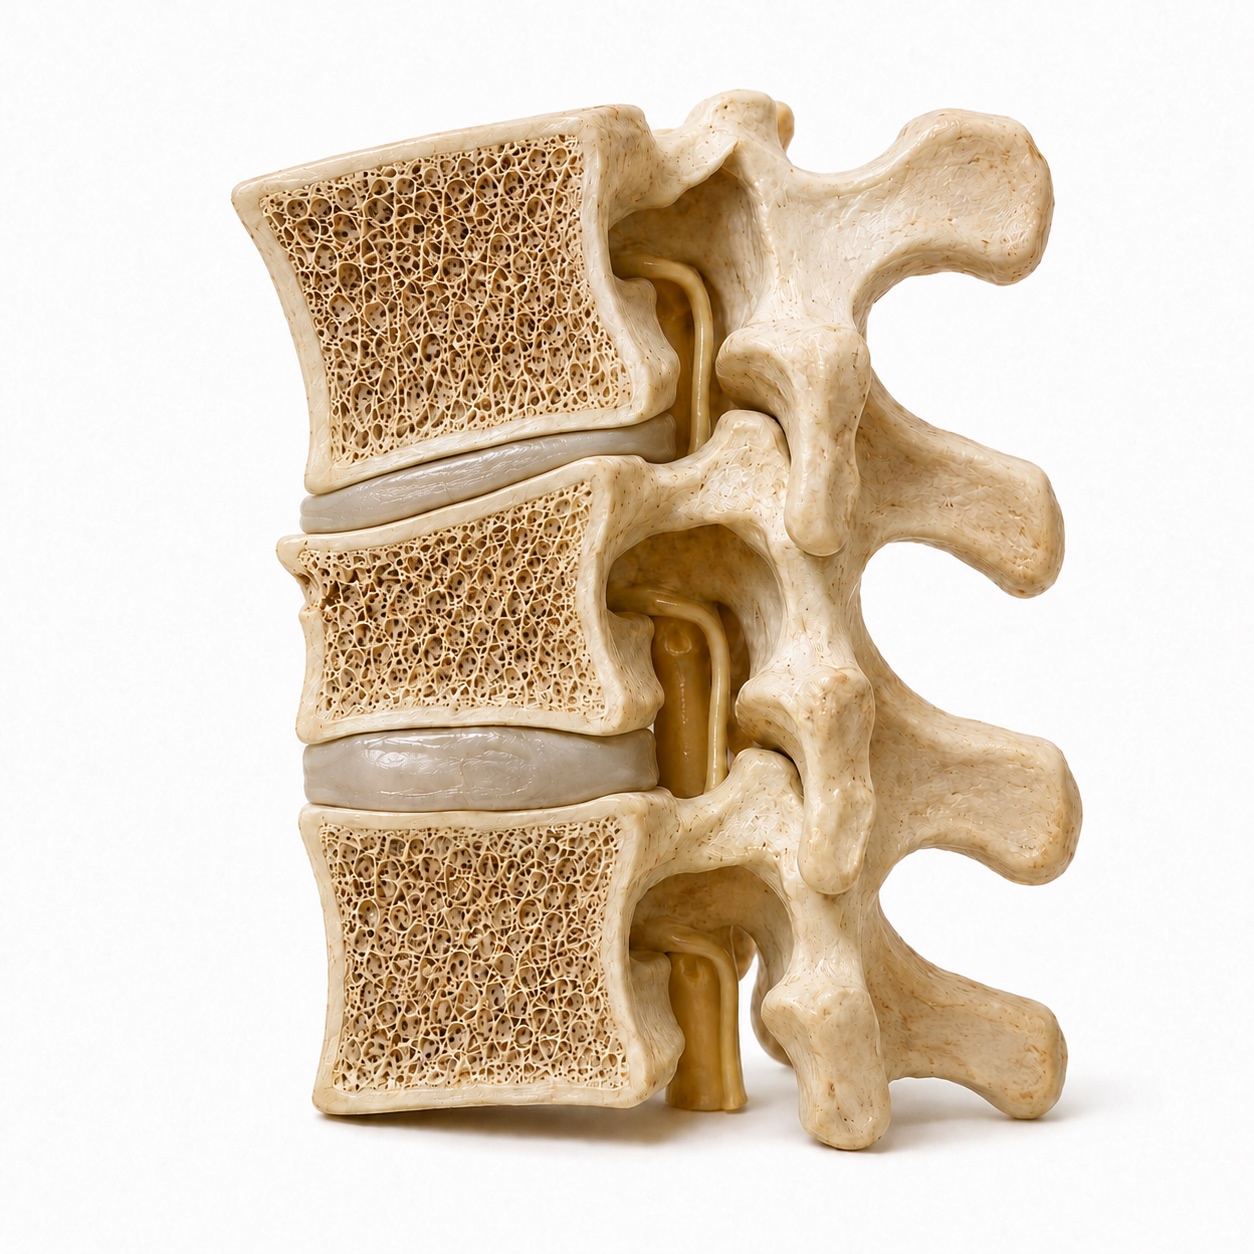
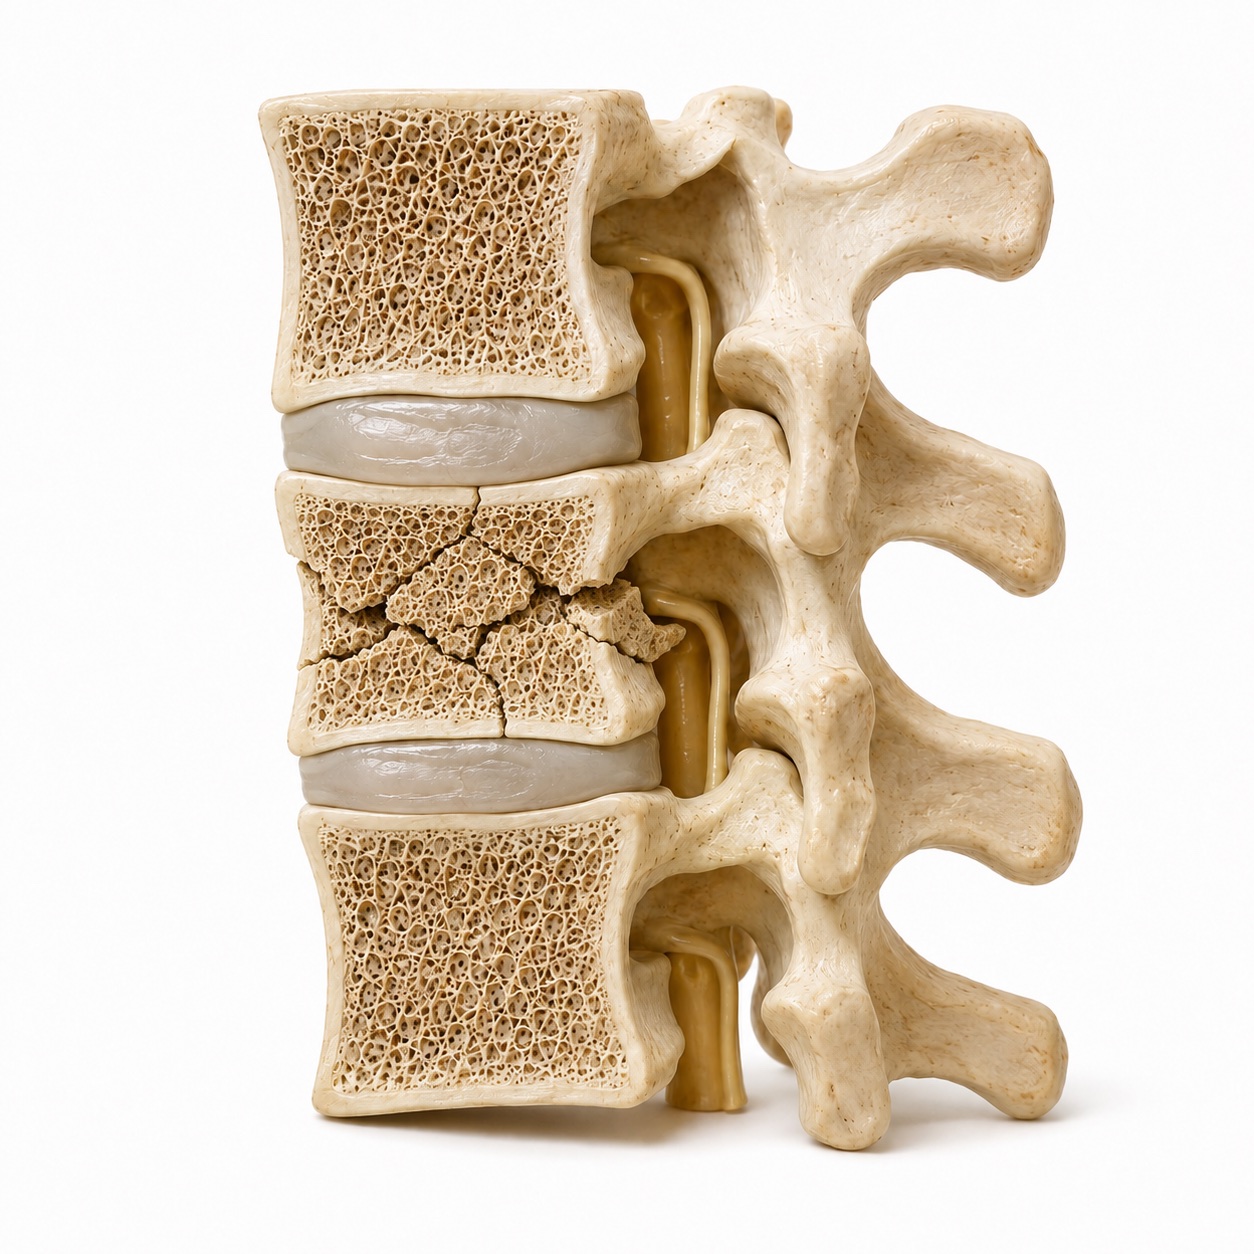
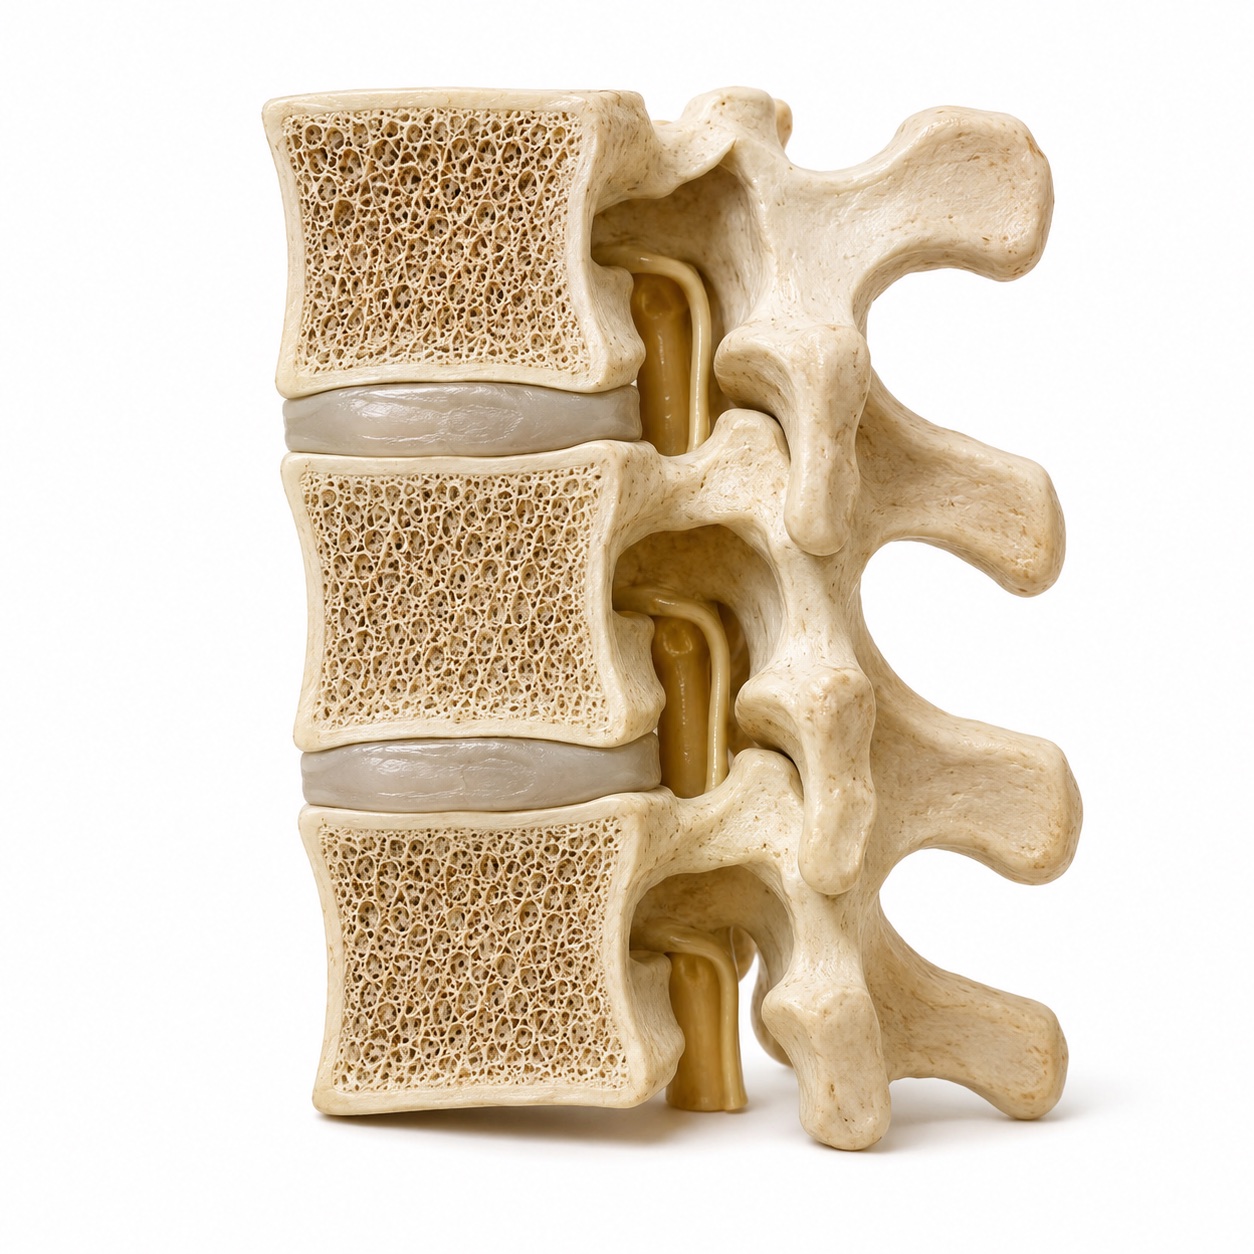
Realistic spine cutaway showing a wedge compression fracture of the middle vertebra, with loss of height at the front and an intact back wall.
Compression fractureThe middle vertebra loses height at the front, forming a wedge.3D educational illustration
Two questions decide everything. Is the spine stable? Are the nerves safe? Those answers come first.
Most stable fractures heal in 6 to 12 weeks. Pain management, activity modification, and sometimes a brace.
The first fracture predicts the next. Every fragility fracture gets a bone-health workup, not just a repair.
Medically reviewed by Jonathan G. Hobbs, M.D. · Updated July 2026
The condition

What Is a Spinal Fracture?

A spinal fracture is a break in one of the vertebrae — the bones that stack to form the spine. By far the most common type is the vertebral compression fracture: the front of a vertebra collapses into a wedge shape, usually in bone weakened by osteoporosis. Higher-energy injuries — falls from height, car accidents — produce different patterns that can threaten the spinal canal.

Is the spine stable?

A stable fracture holds its alignment under normal load and can heal in a brace or with activity modification. An unstable one can shift, and needs surgical stabilization to protect the cord and nerves.

Are the nerves safe?

Fragments pushed backward toward the spinal canal, or any leg weakness, numbness, or bladder or bowel change, turn a fracture into an urgent problem. Getting this call right is exactly what a neurosurgical evaluation is for.

The answers to those two questions separate fractures that heal in a brace from fractures that need urgent surgical stabilization.

Interactive — compare the types

Types of Spinal Fractures

Tap each type to see how the vertebra changes shape, and what that means for stability.

FrontSide cutawayBack
Wedge fracture: the front of the middle vertebral body is compressed while its back wall remains intact.
Wedge fracture — front height lost, back wall intact
Compression (wedge) fracture The front edge of the vertebra collapses while the back holds — producing a wedge. In osteoporotic bone the trigger can be minor: a small fall, a lift, a cough. Painful, but usually stable, and most heal with conservative care while the underlying bone fragility is treated.

3D educational illustrations — not patient scans. Fracture patterns vary; stability is assessed with an examination and imaging.

Symptoms

Symptoms of a Spinal Fracture

Sudden, sharp back pain — often after a fall, lift, or (in fragile bone) a cough or sneeze
Pain localized to one spot, worse with standing or bending, better lying down
Gradual height loss or a new stooped posture (fractures aren’t always painful)
Pain after any significant trauma — car accident, fall from height
Leg weakness, numbness, or bladder/bowel changes — emergency signs
Interactive — quick self-check

Quick Symptom Self-Check

Check any that apply. Educational only — not a diagnosis; a licensed clinician makes all care decisions.

Select any symptoms above to see general guidance.
Treatment

Treatment Options

Fracture care always runs on two tracks at once: heal this fracture, and protect the rest of the spine.

Conservative Care — for stable fractures

  • Pain management and activity modification while the bone heals over 6–12 weeks
  • Bracing when support speeds comfort and protects alignment
  • Bone-health workup — density testing and osteoporosis treatment, because the first fracture predicts the next one

Procedures & Surgery

  • Vertebral augmentation — minimally invasive stabilization of a painful fractured vertebra when conservative care isn’t settling it
  • Surgical stabilization — instrumentation for unstable or neurologically threatening fractures, placed with image-guided navigation
  • Decompression — when fragments compress the spinal cord or nerves

Injured at work?

Spinal fractures are a common work injury. Dr. Hobbs’s workers’ compensation pathway covers authorization, documentation, and return-to-work planning alongside the medical care.

Workers’ compensation spine care
Jonathan G. Hobbs, M.D.
Board-Certified Neurosurgeon · Spine Surgery
American Board of Neurological SurgeryABNS
Certified
The University of ChicagoResidency
Chicago
University of KentuckyM.D.
Kentucky
Why Dr. Hobbs

Why Choose Dr. Hobbs for Spinal Fracture Care

  • Board-Certified Neurosurgeon

    Stability and nerve safety judged by a specialist trained for exactly that call.

  • Elite Training

    University of Kentucky medical degree; University of Chicago neurosurgery residency, chief resident.

  • Least-Invasive-First

    From bracing to augmentation to navigation-guided stabilization — matched to the fracture, not a default.

  • Whole-Spine Protection

    Bone-health evaluation after every fragility fracture — treating the disease, not just the break.

  • Image-Guided Precision

    When hardware is needed, StealthStation navigation places every screw along a pre-planned path.

  • Lakeshore Bone & Joint Institute

    Practicing at Northwest Indiana's most preferred orthopedic and spine practice, with offices in Crown Point & Chesterton.

Frequently Asked Questions About Spinal Fractures

Typically sudden, sharp back pain localized to one spot — worse with standing or bending, eased by lying down. In osteoporotic bone the trigger can be minor: a small fall, a lift, even a hard cough. Some fractures cause only gradual height loss and stooping with little acute pain.
Many do — most stable fractures heal over 6–12 weeks with pain management, activity modification, and sometimes bracing. The essentials are confirming stability and treating the underlying bone fragility, because one osteoporotic fracture significantly raises the risk of the next.
When it’s unstable, when fragments threaten the spinal canal (a burst pattern), or when there are neurological symptoms — leg weakness, numbness, or bladder/bowel changes. High-energy injuries and any fracture with neurological symptoms are treated urgently.
Vertebral augmentation — minimally invasive stabilization of the broken vertebra — for painful fractures that don’t settle, and surgical stabilization with instrumentation for unstable or neurologically threatening fractures. Dr. Hobbs recommends the least invasive option that protects the spine.
A fractured vertebra changes alignment and shifts extra load onto neighbors that, in osteoporotic bone, are already fragile. That’s why care runs on two tracks: heal the break, and treat the bone disease — density testing and osteoporosis management after a first fracture help prevent the next.

A Broken Vertebra Deserves a Specialist’s Eye.

Stable or not? Nerves safe or not? Those answers come first — then the least invasive treatment that gets you healed and protected.

(219) 250-5010

Monday – Friday · 8:00 AM – 4:30 PM

Crown Point Office

500 E. 109th Avenue
Crown Point, IN 46307

Chesterton Office

601 Gateway Boulevard
Chesterton, IN 46304

Your next step

Discuss your spine care with Dr. Hobbs

Jonathan G. Hobbs, M.D. is a board-certified neurosurgeon at Lakeshore Bone & Joint Institute. For questions about spinal fractures & compression fractures, call the office to arrange an individual evaluation and discuss which options may be appropriate.

Consultation offices: Crown Point, Chesterton. Your symptoms, examination, imaging, and prior treatment help guide the discussion.

Request a free second-opinion review

Page updated . About content and medical review dates.